Assisted Living or Nursing Home? Comprehending Levels of Senior Care and Independence
Business Name: BeeHive Homes of Taylor Ranch
Address: 6004 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Taylor Ranch
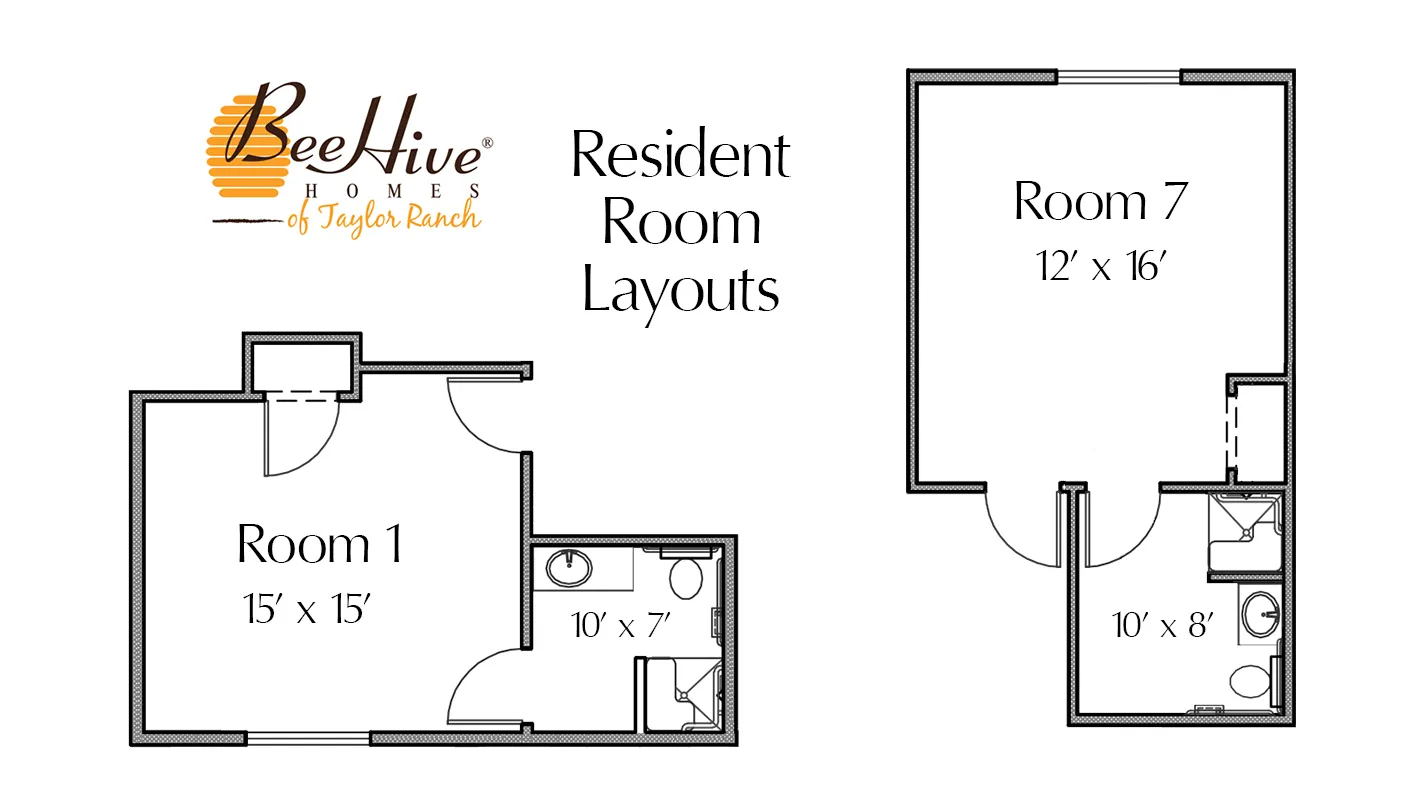
At BeeHive Homes of Taylor Ranch, New Mexico, we offer the finest assisted living experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly elderly care community. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our senior living residents in a loving and respectful manner. We would like to invite you to tour and experience our assisted living home and feel the difference.
6004 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Families seldom sit down to research senior care due to the fact that life is calm and foreseeable. Generally it occurs after a fall, a hospitalization, a dementia diagnosis, or months of peaceful worry that something is not quite safe at home. The language of the senior care system does not help much. Terms like assisted living, proficient nursing, rehabilitation, memory care, and respite care blur together, and you are left attempting to match human requirements to confusing labels.
I have sat at a lot of cooking area tables with adult kids, brother or sisters, and partners trying to arrange this out. The decision in between assisted living and a nursing home is not only about medical care. It touches identity, self-reliance, self-respect, and household finances. Understanding what each level of care in fact looks and feels like daily makes that decision less frustrating and more grounded in reality.
This guide strolls through how assisted living and nursing homes differ, where they overlap, and how to choose what fits a specific individual, at a specific moment, with a particular family and budget.
The landscape of senior care in plain language
Instead of beginning with policies, it assists to begin with what families usually experience.
At the most fundamental level, senior care spans a spectrum:
Home with support: This might be nothing more than family help and a weekly housemaid, or it might include personal caretakers numerous hours a day. When it works, it preserves familiarity and regimen. When it stops working, it frequently fails silently, in the form of missed medications, bad nutrition, unreported falls, or mounting caregiver burnout.
Assisted living: These neighborhoods are designed for individuals who are mainly stable clinically but require assist with daily tasks. Think about dressing, bathing, meals, transport, and medication tips. The environment often looks more like an apartment or hotel than a hospital.
Nursing home (also called knowledgeable nursing facility): These facilities offer 24 hr nursing oversight and more extensive hands‑on care. They are created for people with significant medical or practical needs, often after a stroke, significant surgical treatment, complex chronic illness, or advanced dementia.
Respite care: Short‑term remains in either assisted living or a nursing home so that a primary caretaker can rest, recuperate from surgical treatment, travel, or merely capture their breath.
There are lots of variations within each classification. Some assisted living neighborhoods have actually connected memory care systems. Some nursing homes offer short‑term rehabilitation along with long‑term care. Regulations vary by state or country, which changes what a center is legally permitted to do. The names on the sign are less important than the real services, staffing, and culture inside.
What assisted living actually provides
Families in some cases think of assisted living as "a nursing home with better furnishings." In practice it is a various model of senior care, built around supporting self-reliance rather than changing it.
Most assisted living neighborhoods provide personal or semi‑private houses. Citizens bring their own furniture, photos, and keepsakes. They have a front door that closes, a mailbox, and a sense of "my location." Staff check in, however they do not hover in the corridor outside every room.
Day to day, assisted living usually consists of:
Meals and nutrition support. Three meals a day in a common dining-room are standard. Some houses have small kitchen spaces, however ovens are frequently limited for safety. Staff can generally deal with special diet plans, such as diabetic‑friendly meals or low salt, within factor. If someone forgets to eat or no longer cooks securely, the structure of routine meals can be a substantial benefit.
Help with activities of daily living. This suggests hands‑on help with bathing, dressing, grooming, toileting, and movement. The quantity and kind of assistance is normally laid out in a care strategy and may be priced in "levels of care." A resident might start with minimal help and later need more regular or intensive support.
Medication management. In the majority of assisted living settings, nurses or trained medication aides deal with prescriptions: purchasing refills, setting up med boxes, and administering dosages at scheduled times. For a resident who forgets or accidentally double‑doses, this function alone can minimize hospitalizations.
Basic health monitoring. Staff expect modifications, such as new confusion, swelling in the legs, shortness of breath, mood shifts, or unsteady walking. They are not a replacement for regular treatment however act as an early warning system and liaison with physicians and families.
Socialization and activities. Good assisted living communities invest real effort here. Daily calendars may consist of exercise classes, conversation groups, crafts, spiritual services, outings to shops or dining establishments, and holiday occasions. For elders who have actually ended up being separated in the house, this stimulation can slow decline and lift mood.
Housekeeping and maintenance. Bed linen, towels, cleansing, and building upkeep are dealt with by staff. No more climbing up action stools to alter lightbulbs or worrying about a dripping water heater.
The regulatory authority in your area forms what assisted living is allowed to do. In lots of places, assisted living can not provide intricate injury care, continuous oxygen monitoring, intravenous medications, or consistent guidance for hazardous habits. That is where the line typically starts to shift toward nursing homes.
What nursing homes are developed to handle
The phrase "nursing home" carries a heavy cultural weight. Lots of people imagine a dim ward of lined‑up wheelchairs and buzzing call lights. While there are bad centers out there, the reality of contemporary experienced nursing is more varied.
The essential difference is the presence of certified nursing staff on site around the clock, with the training and authority to manage more complicated medical situations. A nursing home is not just about just how much aid someone requires with bathing or dressing. It is about what takes place if their high blood pressure crashes at 2 a.m., if a feeding tube clogs, or if a pressure ulcer worsens.
Daily life in a nursing home usually involves:
Shared or private rooms. Personal spaces are more typical than they used to be, however they often come at a greater cost and might depend on availability. Shared spaces can impact personal privacy but likewise reduce isolation for some residents.
Intensive personal care. Numerous citizens require aid with all activities of daily living. Personnel offer full assistance with transfers, toileting, feeding, bathing, and turning in bed to avoid skin breakdown. Mechanical lifts might be utilized for transfers when homeowners can not bear weight safely.
Skilled nursing services. This is where nursing homes differ most plainly from assisted living. Examples consist of complex wound care, injectable medications, intravenous fluids or antibiotics, tube feedings, oxygen management, post‑surgical care, and comprehensive tracking for homeowners with heart failure, COPD, or unsteady diabetes.
Rehabilitation treatments. Short‑term nursing home stays often focus on physical, occupational, and speech treatment after hospitalization. The goal might be to gain back enough strength and function to return home or relocate to assisted living. In long‑term homeowners, therapy may be more about maintaining function and preventing decline.
Structured medical oversight. Physicians or nurse practitioners normally visit the facility routinely and are on require immediate concerns. Laboratory draws, imaging, and expert visits can typically be coordinated through the center, lowering the requirement for stressful outings.
Because homeowners in nursing homes are typically more medically fragile, the setting feels more medical. Corridors might have more equipment and monitoring devices. The schedule can be tighter. Yet within that structure, good centers still strive to develop heat and a sense of belonging.
Independence, dignity, and everyday rhythm
The distinction between assisted living and nursing homes is not just a scientific list. It shows up in how life feels.
In assisted living, citizens typically set their own regimens. They decide whether to sleep in or go to the early breakfast, whether to attend the afternoon motion picture or stay in their room with a book. Personnel come by for arranged care tasks, but there is more room for individual preference, even if that choice is, "No thanks, not today."
In a nursing home, more of the day follows personnel workflow, especially around personal care, meals, and medical treatments. When a resident needs 2 people and a mechanical lift to rise, care needs to be collaborated. Shower days may be on a set schedule. Medication times anchor the day. There is still choice inside that structure, however it is narrower.
Dignity does not depend solely on the level of care. I have actually seen assisted living residents dealt with like children and nursing home residents treated with exquisite regard. The culture of the center, the staffing ratios, and the training in person‑centered care matter more than the sign on the building.
Families in some cases idealize self-reliance without acknowledging threat. A person with dementia who "insists on independence" however repeatedly walks outside at night in winter season is not genuinely safe alone. On the other hand, moving a still‑capable elder too early into a more limiting setting can wear down self-confidence and sense of self. The objective is not self-reliance at any expense or security at any expense; it is smart trade‑offs that honor the person's values.
Key differences at a glance
A side‑by‑side view can clarify the landscape, as long as we remember that individual centers vary.
|Aspect|Assisted living|Nursing home (experienced nursing)|| ---------------------------|--------------------------------------------------|-----------------------------------------------------------|| Main focus|Assistance with daily tasks, social engagement|Complex medical care, intensive daily support|| Staff on website|Aides 24/7, nurse availability differs|Certified nurses on website 24/7|| Typical resident|Requirements help with some ADLs, relatively stable|Requirements help with the majority of ADLs, considerable medical needs|| House vs space|Private apartment or condos typical|Mix of personal and semi‑private spaces|| Medical services|Standard monitoring, medication management|Wound care, IVs, complicated meds, rehab therapies|| Self-reliance level|Greater, more personal control over schedule|Lower, schedule formed more by clinical requirements|| Laws & & oversight|Social/ residential care oriented|Healthcare center with stricter scientific policies|
When you tour, focus less on what the pamphlet says and more on who lives there now. If you are bringing your father who still plays bridge and takes brief walks, but most homeowners appear bed‑bound or deeply withdrawn, that setting may not match his existing level of independence.
Where respite care fits into the picture
Respite care is often the unrecognized workhorse of senior care. It describes short‑term stays, typically from a couple of days to several weeks, in an assisted living or nursing home. The goal is to offer a main caretaker, frequently a spouse or adult child, a genuine break.
A common situation: an 82‑year‑old better half taking care of her other half with advancing dementia. He is up in the evening, significantly unsteady, and requires help with toileting and dressing. She is doing whatever, sleeping badly, and slimming down. Their children live out of town. She insists she can "handle a little bit longer" however is noticeably exhausted.
A week or 2 of respite care in a close-by assisted living neighborhood can reset the circumstance. The hubby gets structured care, meals, and activities suited to his level of cognition. The other half rests, attends her own medical consultations, possibly sees old buddies. In some cases she returns home better equipped to continue caregiving. Sometimes she recognizes that a longer‑term transfer to assisted living or a nursing home is necessary.
Respite stays can occur in:
Assisted living, when the person is clinically stable however needs supervision, hints, or aid with day-to-day tasks.
Nursing homes, when the individual requires knowledgeable nursing services or senior living when there is a concern about medical stability.
Respite care can likewise work as a "trial run." Households uncertain about assisted living might schedule a month of respite to see how a parent changes. For some, the change is much easier than expected. For others, it surface areas obstacles early, such as resistance to staff help, unacknowledged incontinence, or advanced memory problems than the household realized.
If you are looking after a senior in the house, integrating respite care every few months can delay and even avoid the need for long-term placement. Caregiver burnout is one of the primary motorists of nursing home admission, regardless of the elder's specific medical status.
Matching requirements to levels of care
There is no single perfect formula, however certain concerns dependably point in the right instructions. When I sit with households, we walk through areas of everyday function and safety instead of beginning with labels.
Here is a compact checklist to help frame the discussion:
- How lots of activities of daily living (bathing, dressing, toileting, transferring, feeding) require hands‑on aid, and how often each day?
- Are there continuous medical treatments or monitoring needs (wounds, IV medications, oxygen, recent strokes or cardiac arrest) that require a nurse's direct involvement?
- Has there been a pattern of current falls, hospitalizations, or emergency clinic visits that recommends medical instability?
- Is there dementia, and if so, does the individual roam, end up being aggressive, or engage in unsafe behaviors that demand continuous supervision?
- How much stress is the primary caregiver under, and is that pressure sustainable for another 6 to twelve months without severe harm to their own health?
If most requires fall in the realm of daily tasks, pointers, and basic guidance, assisted living generally fits. If the answers cluster around complex treatment, constant hands‑on support, or extreme behavioral problems linked to dementia, a nursing home may be the more appropriate setting.
One nuance worth highlighting: some elders technically get approved for a nursing home based upon practical needs but are emotionally even more most likely to flourish in assisted living, particularly with private task care layered in. Others satisfy only the minimum criteria for assisted living but have brittle medical conditions that make closer nursing oversight smarter. This is where experienced geriatricians, geriatric care supervisors, or social workers earn their keep.
Money, insurance, and hard trade‑offs
Family discussions about senior care typically break down at the monetary stage. The costs are real, and the system is complex.
Assisted living is normally paid out of pocket, in some cases with aid from long‑term care insurance coverage or, in some regions, restricted public aids. Monthly expenses vary extensively by area and level of care, however mid‑range centers frequently start in the thousands monthly, not including extras. As a resident needs more help, the costs can climb up in tiers.
Nursing homes may be paid through a mix of private pay, long‑term care insurance, and public programs such as Medicaid, once financial eligibility requirements are satisfied. Short‑term stays for rehabilitation are frequently covered in part by medical insurance, particularly following a certifying health center stay. Long‑term custodial care coverage rules vary.
Families sometimes assume that nursing homes are immediately more pricey since they are more medical. In the personal pay phase, that is frequently true. However, if the older adult ultimately gets approved for a public payer, a nursing home may be the only setting covered, while assisted living continues to require personal funds.
A pattern I see often:
A parent goes into assisted living when still reasonably independent. Over two or three years, care needs increase. Monthly expenses rise to the point that savings begin to diminish faster than prepared for. When the money runs low, the household explores Medicaid and discovers that the guidelines in their state cover nursing home care but just partially cover, or do not cover, assisted living. The parent then deals with a relocate to a nursing home mainly for financial factors, not because assisted living can no longer meet their needs.
Difficult as it is, having frank conversations early about financial resources, eligibility for benefits, and sensible time horizons helps avoid crisis relocations. Involving a certified elder law attorney or a trusted monetary organizer who understands long‑term care can conserve both cash and emotional turmoil.
Family dynamics, feeling, and timing
The choice to move into assisted living or a nursing home is as much psychological as medical. Parents who invested their lives being independent typically resist any tip of "a home." Adult children sometimes postpone tough discussions since they fear dispute or guilt. Siblings argue about whether a mother is "actually that bad yet."
It is common, for instance, for one child who lives close-by and supplies most hands‑on care to push for a move, while an out‑of‑town sibling firmly insists that "she sounds great on the phone." These conflicts are not simply about the parent's condition. They have to do with old family roles, unsettled resentments, and varying tolerance for risk.
A few practical strategies can assist:
Bring objective data into the conversation. Instead of stating, "You are not safe at home," say, "In the last six months you have fallen three times, missed out on medications consistently, and been to the emergency room twice. I am scared you will get seriously injured." Numbers and specific examples minimize the sense of unclear criticism.
Use professionals as neutral voices. Sometimes a parent will accept assistance from a doctor, physical therapist, or social employee that they would reject from their own child. Ask clinicians to speak openly about risks and options.
Try time‑limited trials. A 30‑day respite stay in assisted living or short‑term rehabilitation in a nursing home can shift the discussion from abstract worries to lived experience. People are often amazed by what they like or dislike as soon as they have tried it.
Accept that timing is rarely perfect. Most families either move a little earlier than feels emotionally comfortable, or they wait until a crisis requires the issue. There is no perfect moment where everybody agrees and no one feels clashed. The goal is a decision that can be discussed to your future self with honesty: "We did the best we might with the information we had."
When needs change: moving between levels of care
Senior care is not a one‑time decision. It is a series of changes as health, cognition, and family situations evolve.
Common transitions include:
A move from home to assisted living, with later transfer to a nursing home when medical requirements or dementia progress.
Transfer from medical facility to nursing home rehab, then either back home with support, into assisted living, or into long‑term nursing home care if function does not recover.
Shift within the same community, for instance, from basic assisted living into a protected memory care system when roaming or hazardous behaviors emerge.
When examining a neighborhood, ask what happens if needs increase. Can a resident "age in place" with added services, or is a relocate to a different facility inevitable? Some assisted living communities have strong relationships with home health firms and hospice providers, which can extend for how long a resident can remain there.
Signs that it might be time to re‑evaluate the present setting consist of:
Staff expressing issue that they can no longer securely fulfill needs within their license or staffing model.
Repeated hospitalizations or emergency transfers for problems that could be better managed in a higher level of care.
Significant unaddressed behaviors, such as hostility, wandering into other residents' spaces, or refusal of necessary care, that stretch the capacity of existing staff.
Visible distress in the resident, such as relentless worry, confusion, or withdrawal that may be alleviated in a different environment.
Change is hard, especially for someone currently dealing with loss of home, driving, roles, and health. Yet when handled with respect, clear interaction, and thoughtful preparation, transferring to the ideal level of care can bring back stability and lower suffering for both the senior and their family.
Using details, not labels, to direct decisions
Assisted living, nursing home, respite care: these are tools, not verdicts. The best choice depends on the individual's practical status, medical complexity, support system, choices, and financial circumstance. Labels on sales brochures will not inform you what you actually need to know.
As you navigate choices, take notice of concrete indications: falls, hospitalizations, caregiver fatigue, missed medications, increasing confusion, or without treatment pain. Tour several centers, at unannounced times if possible. See how staff speak to residents. Ask families in the lobby how long their loved ones have existed and what they would alter if they could.
Senior care and elderly care decisions are never simple, however they end up being more workable when you concentrate on levels of support and self-reliance, instead of on fear‑laden stereotypes. Effectively matched care can turn a downward spiral into a brand-new, steadier chapter, where safety and dignity coexist, and where both the older grownup and their family can breathe a little easier.
BeeHive Homes of Taylor Ranch provides assisted living care
BeeHive Homes of Taylor Ranch provides memory care services
BeeHive Homes of Taylor Ranch provides respite care services
BeeHive Homes of Taylor Ranch supports assistance with bathing and grooming
BeeHive Homes of Taylor Ranch offers private bedrooms with private bathrooms
BeeHive Homes of Taylor Ranch provides medication monitoring and documentation
BeeHive Homes of Taylor Ranch serves dietitian-approved meals
BeeHive Homes of Taylor Ranch provides housekeeping services
BeeHive Homes of Taylor Ranch provides laundry services
BeeHive Homes of Taylor Ranch offers community dining and social engagement activities
BeeHive Homes of Taylor Ranch features life enrichment activities
BeeHive Homes of Taylor Ranch supports personal care assistance during meals and daily routines
BeeHive Homes of Taylor Ranch promotes frequent physical and mental exercise opportunities
BeeHive Homes of Taylor Ranch provides a home-like residential environment
BeeHive Homes of Taylor Ranch creates customized care plans as residents’ needs change
BeeHive Homes of Taylor Ranch assesses individual resident care needs
BeeHive Homes of Taylor Ranch accepts private pay and long-term care insurance
BeeHive Homes of Taylor Ranch assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Taylor Ranch encourages meaningful resident-to-staff relationships
BeeHive Homes of Taylor Ranch delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Taylor Ranch has a phone number of (505) 302-1919
BeeHive Homes of Taylor Ranch has an address of 6004 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Taylor Ranch has a website https://beehivehomes.com/locations/taylor-ranch/
BeeHive Homes of Taylor Ranch has Google Maps listing https://maps.app.goo.gl/VjePfgdypFLUTXAZ6
BeeHive Homes of Taylor Ranch has Instagram page https://www.instagram.com/beehivealbuquerquewest
BeeHive Homes of Taylor Ranch has an TikTok page https://www.tiktok.com/@beehivehomesalbuq
BeeHive Homes of Taylor Ranch has an YouTube page https://www.youtube.com/@hamiltonshives4468
BeeHive Homes of Taylor Ranch won Top Assisted Living Homes 2025
BeeHive Homes of Taylor Ranch earned Best Customer Service Award 2024
BeeHive Homes of Taylor Ranch placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Taylor Ranch
What is BeeHive Homes of Taylor Ranch Living monthly room rate?
Our base rate is $6,900 per month. We do an assessment of each resident's needs prior to move-in, so each resident's rate may be slightly higher. However, there are no "a la carte" charges or hidden fees. We do charge a one-time community move-in fee of $2,000
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers, but we are not. We accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved menus with alternates for flexibility, and we can accommodate needs for different textures and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Taylor Ranch located?
BeeHive Homes of Taylor Ranch is conveniently located at 6004 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday thru Sunday: 10:00am to 7:00pm
How can I contact BeeHive Homes of Taylor Ranch?
You can contact BeeHive Homes of Taylor Ranch by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/taylor-ranch/ or connect on social media via Instagram Facebook or TikTok
Conveniently located near BeeHive Homes of Taylor Ranch Flix Brewhouse Albuquerque Coors a great movie theater with full food & drink menu. Catch a movie and enjoy some great food while you wait.